
FIELD REFERENCE
Full criteria & treatment guidance
Stop & reassess
- Remove CPAP for nausea/vomiting, oral/nasal bleeding, intolerance, or systolic BP below 90. PR-120 lists this removal threshold without a pediatric exception, even though its pediatric entry contraindication is below 80.
- Escalate airway/ventilatory support if arrest, agonal respirations, or hypoventilation develops. Watch for gastric distention and aspiration.
BLS and ALS use
- SO-B-001 authorizes OCEMS-accredited EMTs to apply and monitor CPAP. BLS units can use it when equipped and providers are trained and authorized for the device.
- For BLS providers, use particular caution and have ALS en route or already on scene. Monitor continuously and be prepared for deterioration requiring additional airway or ventilatory support.
- Medication and advanced-airway steps must stay within the provider’s own scope. CPAP authorization alone does not authorize independent albuterol administration or advanced-airway placement.
When CPAP is indicated
- PR-120 applies to patients age 8 and older with moderate–severe nontraumatic respiratory distress and at least one qualifying finding.
- Qualifying findings include SpO₂ below 90% despite routine oxygen; respiratory rate above 26/min (above 30 in children) with SpO₂ below 95%; accessory-muscle use/retractions; wheeze, rales, or rhonchi not improving with routine therapy; or fatigue with decreasing breathing effort.
Check contraindications before applying the mask
- Do not use with altered consciousness or inability to protect the airway; inability to sit; respiratory arrest/agonal failure; cardiac arrest; nausea/vomiting; oral/nasal bleeding; suspected pneumothorax; penetrating chest trauma; facial trauma/abnormality; upper GI bleeding; or stomach surgery within the previous month, including lap-band surgery.
- The entry contraindication is systolic BP below 90 in adults or below 80 in children, or other poor-perfusion signs.
Set up the treatment
- Provide oxygen. Albuterol for wheezing requires separate authorization within your scope. Let the patient sit comfortably and explain what to expect.
- Document baseline lung sounds and SpO₂. Assemble the device and connect oxygen.
- Start at 5 cm H₂O. Apply a well-sealed mask and ETCO₂ monitoring; use inline albuterol only when appropriate and authorized within your scope.
- Adults/adolescents: increase gradually to 7.5, then 10 cm H₂O as tolerated and clinically needed. Pediatric maximum: 5 cm H₂O.
Reassess & document
- Continuously observe the patient. Reassess/document lung sounds before treatment, after starting, and every 5 minutes.
- Record initiation time, pressure, vital signs, and consciousness. Notify the receiving ERC early. If removed, document the time and reason.
- A DNR order alone does not exclude CPAP. Use CPAP when the patient otherwise meets the treatment criteria.
Identify the device before setup
- Use PR-120 for patient selection, pressure limits, monitoring and provider scope. Then follow the instructions for the actual device and configuration. Manufacturer flow capacity or a pressure gauge range is not permission to exceed OCEMS treatment limits.
- The examples below are Flow-Safe II EZ with its integrated nebulizer and O2-MAX Trio / Fixed System with Nebulizer. These are different systems. This guide does not establish which device your agency stocks. Confirm its exact model, valve and accessories.
- PR-120 includes pediatric criteria; that does not make every CPAP device suitable for every child. The O2-MAX manuals below specify spontaneously breathing adults over 30 kg. Reconcile patient eligibility with the actual device labeling and agency medical direction.
Mercury Medical Flow-Safe II EZ
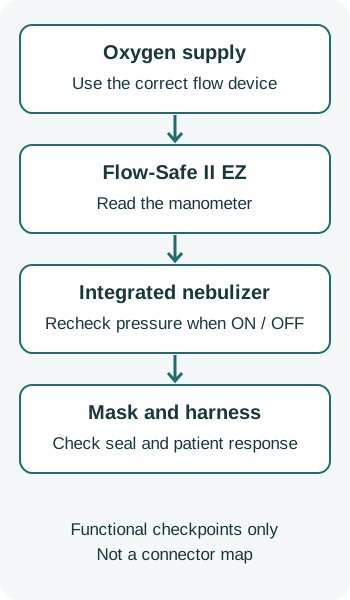
- Connect its oxygen tubing to the gas supply; secure the mask and harness. With the integrated nebulizer OFF, slowly begin at 6–8 L/min and check the mask seal and connections. Adjust oxygen flow to the prescribed CPAP pressure while reading the manometer.
- When a separately authorized nebulized treatment is indicated, turn the nebulizer control ON and recheck delivered pressure; adjust flow as needed. The manufacturer says simultaneous CPAP/nebulization may require a flowmeter capable of up to 25 L/min. Turning the nebulizer OFF also requires a pressure recheck.
- The DFU prohibits flow above 30 L/min. That is a device limit, not a clinical starting flow or target pressure. Use the supplied nebulizer; other nebulizers and flow devices lacking back-pressure compensation may change performance. Continuously monitor oxygen saturation and clinical response.
- The manufacturer lists respiratory arrest, unconsciousness, cardiogenic shock, pneumothorax, facial anomalies/trauma and airway obstruction as contraindications. Apply the full OCEMS exclusions as well. Read the full instructions for additional cautions and specifications.
Pulmodyne O2-MAX Trio
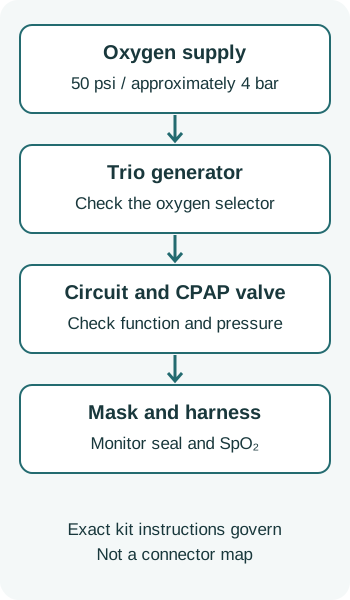
- This manual specifies spontaneously breathing adults over 30 kg and an oxygen supply at 50 psi (about 4 bar). Check for obstruction and correct valve function before securing the mask.
- Trio has approximately 30%, 60% and 90%+ oxygen settings. The selected percentage must be fully visible in its window; a partly positioned setting may deliver about 30%. Monitor SpO₂ continuously and follow local oxygen targets.
- Check the circuit, mask seal, CPAP valve and pressure during inspiration. The manual warns that an obstructed valve can impair exhalation. If oxygen flow stops, remove the mask and provide appropriate support. The gauge range is not an OCEMS treatment pressure.
O2-MAX Fixed System with Nebulizer is a separate configuration
- Manual 2764G describes an adult-over-30-kg fixed system using 50 psi oxygen and approximately 30% inspired oxygen. It does not have Trio’s three-setting selector.
- For the pictured manual’s nebulizer configuration, connect the canister supply tubing to oxygen; remove the port cap, insert the canister and secure with a quarter turn. Set nebulizer gas flow and confirm aerosol. The manual does not provide a universal numeric nebulizer flow here; do not borrow Flow-Safe II EZ settings.
- Check the exact kit’s full instructions for its filter, valve, contraindications and monitoring. Verify independently authorized medication and dose.
O2-MAX Fixed System with Nebulizer instructions (June 13, 2022) ↗
VISUAL FIELD REFERENCE
CPAP pressure: keep the age groups separate
Adult / pediatric age 8+ · BLS / ALS
Start at 5 cm H₂O only after checking the full indications and contraindications below.
- 5 → 7.5 → 10 cm H₂O
Adults / adolescents
Adults/adolescents: increase gradually to 7.5, then 10 cm H₂O as tolerated and clinically needed.
- 5 cm H₂O maximum
Pediatric patients
Pediatric maximum: 5 cm H₂O.
- PR-120 applies to patients age 8 and older with moderate–severe nontraumatic respiratory distress and at least one qualifying finding.
- Remove CPAP for nausea/vomiting, oral/nasal bleeding, intolerance, or systolic BP below 90. PR-120 lists this removal threshold without a pediatric exception, even though its pediatric entry contraindication is below 80.
Selected checkpoints; read the complete guide for criteria, exclusions, doses, and ongoing care. PR-120 · SO-B-001
UNDERSTAND THE CARE
Why applying CPAP starts a monitoring task
CPAP requires a patient who meets the clinical criteria and can continue protecting the airway and tolerating the mask. Eligibility is therefore not a one-time checkbox. Observe consciousness, breathing effort, pressure, oxygenation, mask seal and tolerance continuously, with the documented reassessment intervals in the procedure.

Applying the guidance
The clinical pressure order and the device’s oxygen supply instructions answer different questions. Verify the exact system and its manufacturer instructions instead of borrowing flow settings from another model. A change in nebulizer configuration can change device performance and requires a pressure recheck. BLS authorization to apply CPAP does not independently authorize the medication used in a circuit.
Putting it together
Teaching example: the mask seal looks good but the patient becomes less responsive or begins vomiting. The initial eligibility no longer establishes safe continued CPAP; follow removal and airway-support instructions promptly.
Diagram text & teaching checkpoints
- Patient fit
- Age, airway, breathing, pressure and exclusions.
- Device fit
- Exact model, supply, valve and configuration.
- Delivered support
- Measure pressure; do not infer it from gas flow.
- Response
- Continuous observation and explicit stop criteria.
Sources for this explanation
Original OCMedic teaching synthesis of the references below. Educational expansion updated ; this is not a new independent clinical-review date. Source-specific dates and limitations remain in the full guidance.
- PR-120 — Continuous Positive Airway Pressure (CPAP)
- SO-B-001 — Basic Life Support Standing Orders
- 310.00 — 9-1-1 Advanced Life Support Base Contact, Standing Order, and Transport Criteria
- Mercury DFU — Flow-Safe II EZ instructions, Rev. 8 (September 2024)
- Pulmodyne 2260F — O2-MAX Trio instructions (June 13, 2022)
- Pulmodyne 2764G — O2-MAX Fixed System with Nebulizer instructions (June 13, 2022)